Sunday, 20 December 2020

Case Based Blended Learning Ecosystem on FHIR

In 2016 I had built a basic version using WordPress for implementing UDHC/CBBLE (presented at AIIMS Delhi in Jan. 2017), and then created this mockup of an app. My involvement in UDHC project (CBBLE is a subset and key element in UDHC system) helped me explore EBM and parallelly HealthIT in-depth finding my way to learn more and connect with amazing HealthIT evangelists globally and currently I am even having some experience in volunteering for HealthIT & FHIR projects and thankful for the opportunities to DHIndia and HL7India.

3 years back I had plans to learn implementing FHIR for this project for making this an interoperable platform and then help to evolve the ecosystem of various UDHC networks (mainly in medical schools) as I have a great interest in the UDHC idea. The journey is still going on with various volunteers, peer learners and mentors including Dr. Rakesh Biswas who pioneered the UDHC concept. He provides the opportunity to many students including me to explore the idea and implementation while benefitting the patients too. 

It was inspiring to find FHIR community have started implementation for case-based learning in the webinar by HL7 International "Case-Based Learning (CBL) on FHIR December 16, 2020 | 4:00 - 5:00 PM EST" and I am hopeful that the ecosystem will evolve more helping medical students and professional to be able to deliver better to the patients.  https://pubmed.ncbi.nlm.nih.gov/32025640/


Long way to go.


DISCLAIMER: Below are some videos, HAVING CLINICAL IMAGES AND DATA SO MAY NOT BE SUITABLE FOR SOME AUDIENCE.

Resources -

  1. OpenMed app mockup - https://github.com/avi33tbtt/OpenMedApp/blob/master/OpenMed.pdf

  2. Digital Health Records for Medical Education - https://www.youtube.com/watch?v=rWog_idt-KU

  3. Patient As A Teacher - Developing a Case-Based Blended Learning Ecosystem CBBLE - https://youtu.be/xvE5b8Xk3vM

  4. UDHC (User-Driven Healthcare) - https://classworkdecjan.blogspot.com/2020/01/udhc-resources.html

  5. A Futuristic EHR - https://youtu.be/yrJ0DfmRg8E (I am yet to write the explainer blog as could not record the video when it was presented offline, will do it in coming weeks and update here).

  6. Link to apply for electives under Dr. Rakesh Biswas - https://promotions.bmj.com/jnl/bmj-case-reports-student-electives-2/ (not necessary to have healthcare background)


 https://github.com/avi33tbtt/OpenMedApp/blob/master/OpenMed.pdf

Friday, 30 October 2020

Translating and Sharing a research paper to a patient

 Translating and Sharing a research paper to a patient 

1) open article in pubmed

2) on right side, click for PubReader format

3) Copy title and content of the Case Report (or research article)

4) Paste in a blank google docs

5) In google docs click on tools and then translate and choose your patient's langiage

6) Click share and then share to patient's email id or print to provide as paper document.

7) Can do corrections if needed, as translation tools are not 100% accurate but as they are very efficient, corrections may not be necessary. (It is recommended to have corrections and utilize for sharing copies to any number of patients.)

8) Ask the patient to highlight/comment and ask questions with you for clearing doubt online or in next consult or in meeting with patient group.


Patient themself can also follow the above way.


Patients must note that it is for learning and not for self-diagnosis or modifying treatment plan. The knowledge gained will help to better participate in own care process and make patient and doctor more impactful in care delivery. Doctor's must note to explain patient this point clearly.

There may be challenges with IP, and they should be solved by looking for best possible and articles shareable this way.

Saturday, 29 August 2020

Use of a telemedicine registry

Since decades there were huge efforts by various govt. agencies , academia, and industry on not only implement telemedicine but scale it. Though some implementation happened, scaling was rare. Covid have made life very tough for many who seek care, some times made it nearly impossible to visit hospital and get help from the doctor. Those in any acute pain or mild problems suffered, those suffering chronic problems also suffered and got no follow ups, patients needing dialysis or patients who need Hydroxychloroquine suffered due to inaccessibility or shortage, the pregnant moms suffered by missing their important regular checkups, small kids missed their vaccinations and even those who got access to hospitals suffered by not having access to better and some suffered due to stress this pandemic have created in daily life. 

Telemedicine which includes tele-consultation, tele-Icu, etc can not solve all the patient problems but surely it easily and efficiently solves many of them and reduce patient's suffering during this pandemic and empower everyone for better with the new normal. It have capability to help bring relief to a patient having mild acute problem somewhere, to bring access to care in patient in remote rural place, to bring support for follow ups when hospital visit is not necessary, to empower for second opinion from another doctor somewhere, to empower ICUs by support from remote center, and a lot more. Having a Registry where Tele-medicine products are listed after evaluation from an expert panel will help the patients, doctors, hospitals, tele-medicine companies and all stakeholders in the tele-medicine ecosystem by having access to information about various products, their capabilities, their strength and weaknesses. These key information will help decision makers to find products best suited to them and accelerate the adoption which will directly accelerates the empowerment of our healthcare system in country by making impact in solving many patient problems like those listed above and reduce their suffering. It will also help the ecosystem with a direction that helps to innovate and improve for delivering better.

I am not emphasizing in the context of Covid pandemic much because I have first hand experience in being helpful to patients and also engage with doctors offering telemedicine to patients globally (and tele-education which is equally important for our country) for 3 years even before the pandemic began and so i believe in its tremendous capability not just for war against Covid but even beyond the pandemic.

I am currently involved in Tele Med Registry http://telemedregistry.in/ as student member of DHIndia.

I would also like to share a playlist I have made by compiling a few useful videos in youtube, which helps to understand good webside manners and physical examination on the webside which are very important in the care process. If you are interested then can check on this link - http://classworkdecjan.blogspot.com/2020/08/telemedicine-good-webside-manners-and.html

Telemedicine - good webside manners and physical examination

 "The whole art of medicine is in observation" - William Osler


Physical examination is very important in for doctors to get insights from the patients and find correct diagnosis and best treatment plan. Teleconsultation software nearly always have the physical examination as part of the clinical workflow but doing it well may be a challenge for the care providers.


So I made this youtube playlist which may help with tips on doing physical examination and following good webside manners. I hope this will be useful in covid times and later.


link to the playlist -  https://www.youtube.com/watch?v=4hRObfNyDvc&list=PL7NbfQr9rYIeU2GUIKLF4F-4DfpqZATMW

Tuesday, 25 August 2020

Email to Medical Education Unit (India) email group.

To - meu_india@googlegroups.com


Respected Teachers


Using paper based forms and then digitizing data to analyze is a painful task. Here is a google form I have made with guidance from Prof. Rakesh Biswas (KIMS, Narketpally) which you may copy and use for your students feedback. A Students need to fill form once for each subject. 


Form - https://forms.gle/AbD5feAAbu1241CN6


There are 2 ways this form can be used


1. You can send me a request on avi33tbtt@gmail.com so i can help you get a copy of this form which you may use to get feedback, get basic automated analytics and do advance analytics yourself if needed. Based on your need you can also make modifications to the form.


2. You can help us by sharing the above form link to your students so we get nationwide feedback data where no student identifier is recorded as all data is collected anonymously and we share the analytics openly. It can also be used for research purpose. 


Doing both also possible, all you need is to follow the first way and then share data with your consent (without any student identifiers) to include as data for national level analytics.


Regards,

Avinash Kumar 


Reply to teachers requesting form -


Respected Sir/Madam,


Thanks for your interest in Online Medical Education/Classes Feedback Form.


I am sharing this form with you and giving you owner access. You may then distribute this form to students using this link - https://forms.gle/************


If you wish to add any more questions like roll number, email id of student etc. then please let me know, i will be able to update accordingly. 


knowing roll numbers will help to know about which students haven’t filled the form and hence you can instruct them later to fill if pending, without roll numbers it won’t be possible to identify students pending to give response so you may prefer to add that field, please let me know.


Once you are ready to go ahead for sharing the form, you can remove my access to the form if you need. Please let me know in reply to this email, if you also want to share your student’s feedback data for national level analysis on Online Medical Education/Classes.


Regards,

Avinash Kumar


Thursday, 23 July 2020

38yr old woman - Renal failure on MHD

This is a de-identified open-online-patient-record with initial information in patient's voice, posted here december 2016 after collecting informed patient consent (form downloadable here) by BMJ Elective Student.

Patient history by author -__

38 year old woman from ******* currently on hemodialysis in our hospital for renal failure.
She has been having a struggle  life since 1995 when her mother passed away due to a medical condition ( reason not known by the patients husband)  who was a known diabetic and a known hypertensive. In 1998, her father passed have because of an unknown cardiac condition. She got married in 2000 to her husband who works at a rice mill industry. She has 2 daughters, the elder daughter is 19yrs of age and currently in her btech 2nd year, 2nd daughter is 17yrs old and is in her inter 2nd year.
In 2006 she paid a visit to her dentist for getting a  rootcanal done that was when she got diagnosed with type 2 diabetes mellitus and was put on Tab Zoryl 2mg BD. She has been switching from Tab Zoryl 2mg to 1mg depending on her blood sugar levels on her own .
6 yrs back, her husband had to sell their *** store ****** because of road construction work, since then her husband says she has been more stressed and she would randomly throw tantrums It had got to such a point that she would throw objects aggressively at others and over the past 5 years she has also been having visual and auditory hallucinations. She was taken to a psychiatrist in **** (  hospital) and the doctor there started her on tab Sizodon Forte ( risperidone and trihexyphenydryl ) and Tab Dayo 250mg ( Divalproex) and they even consulted a neurophysician who advised for a CT brain which turned out to be normal. She got diagnosed to be a hypertensive 3 yrs back and has been using Tab metxl 25mg once daily on and off since then.
One and a half years back she consulted an obstetrician since she had amenorrhea since 3 months, her husband says that he even found her to be pale then and on routine investigations she got diagnosed with renal failure with a serum creatinine of 5mg/dl and Sr urea of 70mg/dl for which they consulted a nephrologist who started her on sodium bicarbonate and calcium supplements.
1 month back she presented to our hospital dyspneic with bilateral pedal edema extending to her thighs for which she was started on hemodialysis.


Day1 post admission
-


Day 3 post admission
-


Day 4 post admission


Patient history by author -VV

38yr old woman
Renal failure on MHD
S - Complaining of non productive cough and aggravated dyspnea since last night.
She also complains of feeling febrile since last night.
O - Patient is pale and bilateral pedal edema present
Patient appears to be in respiratory distress
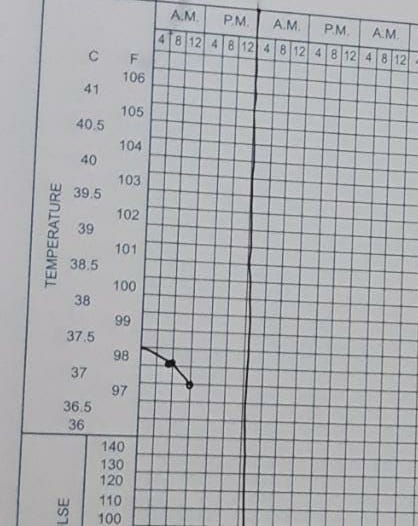
- PR-99bpm
BP- 120/80mmhg
Spo2-98% at 2 litres of oxygen
RR-24cpm
Cvs -S1 S2 present
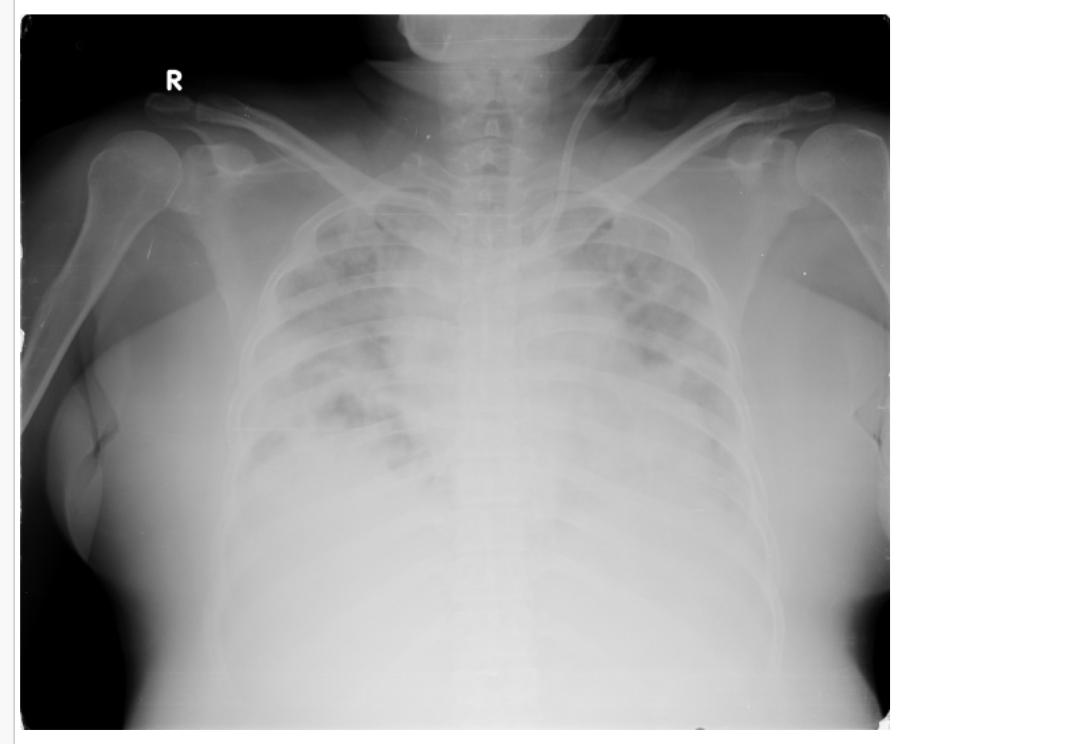
Lungs- bilateral inspiratory crackles present
Abdomen-distended with everted umbilicus
A- ckd on mhd
Type 2 diabetes since 15 years on medication
Htn since 3 years
Schizophrenic since 5 years
? Pulmonary koch’s / ? Septic emboli
P- 2D ECHO in view of any infective endocarditis changes
Sputum for cbnaat to be sent
Coagulation profile to be sent
Debate on whether to start on antitubercular therapy


Conversational Learning/CDSS -


AT- Palpable skin lesions with Cavitary lung lesions and rapidly progressive renal failure. All roads lead to Rome (GPA in this case ?)
RB- Someone still has to carve out a generous amount of lung tissue from her to prove that Rome exists? 😅
AT- In an ideal non covid world, yes sir. However, a skin biopsy with cANCA titres would be helpful here.
RB- Or can we take a short cut to Rome through her skin tissue which would be more easier? 🤔
AT- What would you expect in the skin biopsy that would take us to Rome conclusively?


AT- Necrotizing granulomatous vasuclitis. I think I saw rim enhancement of the cavity walls in the CT and also the renal lesion appears aggressively active. Some system 1 learning says cANCA in active inflammatory lesions is strongly positive and suggests a small vessel vasculitis, particularly GPA.

RB- What would be the sensitivity and specificity of this finding?

Enough to consider immunosuppresives over Sepsis treatment as both are antithetical to each other
AT - Even a renal biopsy showing pauci immune glomerulonephritis can help. Will share some system 2 data.


AT - https://www.ncbi.nlm.nih.gov/pmc/articles/PMC5059091/#!po=0.943396

Between February 1, 2005 and February 1, 2015 a total of 8403 IIF for ANCA was performed of which 1238 tested positive (27% p-ANCA, 71% c-ANCA pattern, 1% aspecific pattern) in 279 patients. A total of 5370 immunoassays for PR3 and/or MPO ANCA was performed of which 1218 samples tested positive in 239 patients (Fig.1)


RB - Can we fit our patients to any of the patients in the study you quoted here?

What are the attributes she shares with them?

AT-


- The table explains quite a lot. Patients were initially diagnosed on clinical features and then ANCA samples were sent for.
RB - Looks reassuring.


DV -https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4014960/


FIndconsult app project - closing

about swasth alliance -> "The idea is to provide free consultations as far as the corona pandemic is concerned and get as many doctors onboard to make sure that the healthcare infrastructure in the country is not overburdened by leveraging technology”.

i worked on same idea in very frugal way where patient had access to doctor directly in 1 click on social media platform. In case of emergency may be that was/is urgent beed to solve. I am happy to see it being done much better way than mine. I recently explored their APIs where they are building the registry part to verify doctors giving consult which in my case was one of the main reason for avoiding full launch of project as i had no full proof mechanism for that and it will be bad to make a platform for quackery, also one problem was securing doctors contacts as i was using one click access to list of currently online available doctors for free consult using social media platforms but as many doctors wanted to help and were circulating their contacts for helping people, it was ok to go ahead as more benefit than risk.

this website is down now, i have code, and here is the demo -

https://youtu.be/APAaIXCr2PQ

(there are various cons in  this way, it is less of a HIT work and more of a disaster medicine response.)